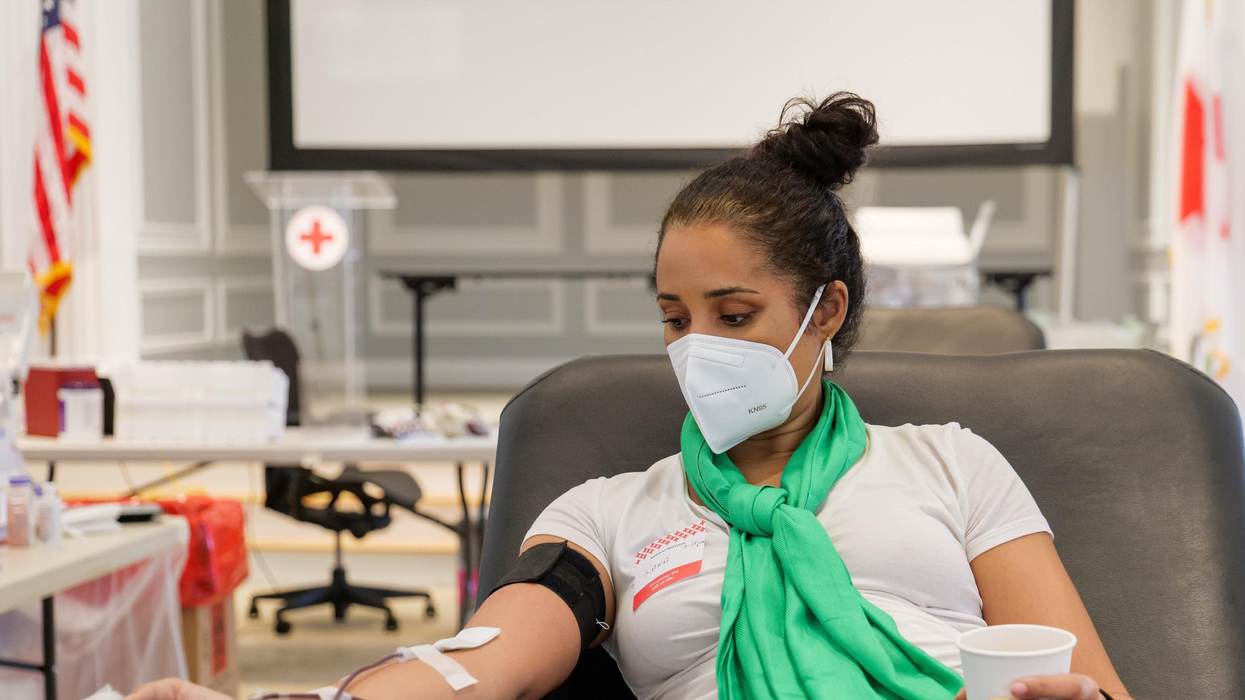
When you give blood, you're actually giving several products that can be transfused into several different people for various reasons. Blood is composed of plasma, platelets and red cells. All blood donations are processed and available for use approximately 24 to 48 hours after donation. After processing, red cells can be stored for 42 days, plasma can be frozen and stored for up to 12 months and platelets (from whole blood or by apheresis) expire after 5 days and are stored at room temperature.
Blood Components & How They Are Used
- Plasma is the watery fluid that transports cells and replaces blood volume. It is required to maintain blood pressure and assist in clotting. It also contains proteins that may help fight disease.
- Platelets are proteins that help blood clot. They are transfused into patients undergoing transplants and those with leukemia and other cancers.
- Red cells carry oxygen. They are transfused into patients with anemia, and those who have lost blood during surgery or trauma.
| Blood Component Use | Units* |
| Automobile Accident | 50 units of blood |
| Bone Marrow Transplant | 20 units of blood
120 units of platelets |
| Heart Surgery | Six units of blood
Six units of platelets |
| Organ Transplant | 40 units of blood
30 units of platelets
20 bags of cryoprecipitate
25 units of fresh frozen plasma |
*Average usage.
Autologous Transfusions
Autologous blood donation, in which you donate your own blood for use during a surgical procedure, was quite popular in the early 1980s when the risk of HIV infection was very real. But today it's not worth doing if your community has an adequate blood supply. Although autologous donations can spare you some of the very low infectious risks of using the available blood supply, from a cost/benefit standpoint it's a very expensive option to prevent a very few bad outcomes.
Half of all autologous donor blood doesn't even get used and must be discarded. Plus, even if you donate your own blood, you may still have a reaction during the transfusion. Or, your donation could get mixed up with someone else's and used for the wrong patient.
Overall, experts agree, the safest alternative for medically needed transfusion remains your own blood, but, in most cases, this option adds very little from a safety perspective. Still, if you want an autologous blood transfusion for your own peace of mind, all blood centers offer the option.
Are Transfusions Necessary?
One of the simplest ways to stretch the tight blood supply might be changing physician practices about when patients should get transfusions. A growing body of scientific literature suggests that some transfusions might not be necessary. Traditionally, most doctors have transfused patients when their hemoglobin levels drop to 10 g/dL. Today, many doctors think the decision of whether or not to transfuse should be made in the context of other factors as well, including the patient's symptoms and overall health.
Reducing the number of blood transfusions this way could increase the nation's blood supply, making blood more readily available to those in need. To move hospitals in this direction, some blood centers have full-time "transfusion safety officers" who work with hospitals on these and other transfusion-related items. But patients can also play a role, say experts, by asking their doctors: "Is this transfusion necessary?"
Risks of Blood Transfusions
Transfusion errors pose a small but significant risk to patients, occurring at the rate of two errors a day nationwide, on average. And no one really knows how many result in death, since, until fairly recently, hospitals weren't required to report transfusion-related errors that did not result in death. Between October 1, 2005, and September 30, 2006, the FDA received 81 reports of fatalities in patients receiving blood transfusions. Of those, eight were unrelated to the transfusion, 63 resulted from the transfusion, and the other 10 causes of death were undetermined. Yet even if it doesn't result in death, any kind of reaction to the wrong blood can slow your recovery and increase your risk of complications.
The primary reason for most blood-related errors is human mistakes. For instance, the sample from the patient may be mislabeled with another patient's name before it is sent to the lab, and then the wrong unit is sent to the patient for transfusion. Or, in the heat of crisis in the emergency room, someone forgets to double-check a patient's identity and match it with the label on the unit.
To avoid these errors, some hospitals have begun implementing bar code systems for blood transfusions, in which nurses use a scanning wand like those used in grocery stores to make sure the code on the blood matches the code on the patient's bracelet.
In addition to your risk of getting the wrong blood, other risks include bacterial contamination of blood products and a condition called "transfusion-related acute lung injury," a serious pulmonary syndrome that can lead to death if not recognized and treated appropriately. The syndrome is believed to be the third most common cause of blood transfusion-related death. There is also some concern that transfusion may affect the immune system and cause some mild immune suppression.
For these and a multitude of other reasons—not the least of which is the chronically short blood supply—researchers have been scrambling to discover "artificial" blood products and means of maintaining blood products longer. Various types of hemoglobin carriers are being studied, but approval is unlikely in the foreseeable future because of safety concerns.